Tipped employees are opposed, because they make far more than $25 per hour in tips. This will kill many jobs and cause prices to skyrocket, which will force places to close. Want to know why a hamburger at McDonald’s costs $12? This is why.
A 538 FICO score, trying to get himself a Mercedes with what I presume is his IRS check. The finance guy says $8k down is the minimum to get approved for 19.99% interest and $700 payment for 4 years.
Thing is, there is a roughly 40% chance of a default within the next 3 years with that FICO score. The interest rate has to reflect that.
The Washington state legislature just passed a law making it a felony to possess digital files that can be used to make any part on a CNC or a 3d machine that could potentially be used as a part of a firearm.
Not only impossible to make work in any practical or Constitutional sense, it opens a huge can of worms.
The US isn’t built on magic dirt. Third world savages don’t become part of US culture merely because they touch our soil. Immigrants CAN be great Americans, but you have to be selective in who you allow in, or this is what you get.
Proving once again that, if it weren’t for double standards, the left would have no standards at all, Virginia has passed a law that defies belief. It is now a crime in Virginia for a school to “state, suggest, or present as credible a statement or suggestion that there was extensive election fraud that could have changed or actually changed the results of the 2020 presidential election.”
Not only that, but the same law says that school instruction must “Describe the January 6, 2021, insurrection at the United States Capitol as an unprecedented, violent attack on United States democratic institutions, infrastructure, and representatives for the purpose of overturning the results of the 2020 presidential election.”
Not only is this law egregious, but CBS’ reporting of it is as bad. The reporting here would have made Goebbels or Zhdanov proud. First lie is in the headline:
Virginia passes legislation prohibiting schools from teaching falsehoods about Jan. 6 riot
Read the money quote:
The White House posted a series of lies about Jan. 6 on an official federal government web page on Jan. 6, 2026, including a bogus claim that police bore responsibility for the attack.
So is telling teachers to teach only one side of a story propaganda, or not? A First Amendment issue, or not? Wouldn’t it be better in a politically charged case like this one, to present both sides and let students decide for themselves? Are we teaching students how to think, or what to think?
“Who controls the past controls the future: who controls the present controls the past.”
“The party told you to reject the evidence of your eyes and ears. It was their final, most essential command.”
“All propaganda is lies, even when one is telling the truth. I don’t think this matters so long as one knows what one is doing, and why.”
“The president had the constitutional authority to direct the use of military force because he could reasonably determine that such use of force was in the national interest.”
The next liberal who complains about the Iran conflict, ask them if the above quote is an accurate description of Presidential powers. If it isn’t, what should happen to the President making this claim?
Nursing is a great job because it’s a large tent. There are jobs for nurses both in and out of hospitals. I can’t speak for out of hospital nursing because I don’t have any experience whatsoever, but in hospital there is a hierarchy, and it’s the same in nearly every hospital, to the point that memes are made about this.
Nursing has a definite pecking order. Let me say that each nursing specialty is needed, but some nurses do have a more strenuous pathway than others. Remember that nursing is filled with mostly women (about 65% female) and women are some catty, backstabbing bitches. It makes for some very cat-like behavior, and not in a good way. No, in a “mean girls” way. The bullying and competition is pretty fierce. Women are simply vindictive, conniving bitches.
You have your inpatient nursing- medical/surgical (called med-surge), and these nurses staff the oberservation and general patient floors. Generally, med-surge nurses care for the least complicated patients, and they tend to be the least skilled nurses in the hospital. I’m sure that will piss some people off, but that’s just how it is. Because the patients are low acuity, nurse/patient ratios are 1:6 or sometimes as high as 1:8.
A step up from that is cardiology, oncology, wound care, those sorts of specialties. Nurses in these areas are very good within their specialty, but don’t generally know a whole lot outside of it. Again, they are needed, and a great example is that I suck at wound care, so not slamming anyone. The nurses in this area are usually ratioed at 1:4 or 1:5.
Above the general floor nurses are your step down units- PCU, CVPCU, those kinds of units. These nurses handle patients that are more complicated and require more care. For that reason, ratios are usually 1:3 or 1:4.
The next level up in the inpatient nurses packing order is the ICU. The nurses in this unit generally consider themselves to be the cream of the crop. There is a bit of a superiority complex here, and a good bit of it is well deserved. ICU nurses are well known for being very detail oriented and for having OCD. Every IV line is carefully labeled with color coded stickers. The ICU nurse knows everything there is to know about the patient: the name of his kids, his dog, his favorite color. They have time for that, because the nurse patient ratios are frequently 1:1 or 1:2, so they spend the entire 36 hour workweek with 1 or 2 patients.
Then there are outpatient nurses. PACU (post anesthesia care unit) nurses take care of patients who have just come out of surgery. After that the patient either gets admitted to an inpatient unit, or goes home. Also surgical nurses, endoscopy nurses, and the like. The nurses here are fairly specialized, and most of them work M-F 9-5 jobs. Other nurses refer to these types as “princess” and the shifts they work are called “princess shifts.”
The emergency department. The nurses here are known as being “cowboys” who don’t follow the rigid rules the rest of the hospital’s nurses have to follow. They have one overriding goal- stabilize a patient, then send them to an inpatient unit. Everything else- bathing the patient, changing their clothes, and other nursing tasks just don’t get done. ED nurses also tend to think of themselves as being the best of the best, and act like those routine tasks are beneath them. For this reason, inpatient nurses generally don’t like ED nurses.
If anything goes wrong in an inpatient nurse’s area, the nurse will initiate a “rapid response” or “CAT” call, and the response team will come to help them out. Some hospitals use ICU nurses as the response team, other hospitals use ED nurses.
As you can imagine, the rivalry between ICU and ED nurses can be rather intense, med-surge nurses feel (or are looked down upon) as being inferior, and the entire hospital feels like it is at war with one unit, shift, or zone being at war with all of the others. Some temporary alliances are formed, mostly when one unit teams up with another to take a third unit down a peg or two.
Yes, nursing is filled with a bunch of infighting that is mostly caused by having several hundred women in the same building, all wearing the same outfit, and about 1 in 5 of them is menstruating at any given time. It’s like being in a building full of rabid honey badgers.
All shift long, it’s “day shift is lazy,” or “Night shift didn’t do anything last night,” then you hear “Med-surge nurses are idiots,” or “Those ICU nurses are stuck up bitches,” and the old reliable “The ED nurses didn’t even bathe this patient and put him in a gown before they sent him up.”
Older nurses take great pleasure in screwing with younger ones, for no other reason than flexing their pecking order muscles. It’s so bad that every nurse hears an old adage while they are in school: “Nurses eat their young,” meaning that the level of bullying of new nurses by old ones sends many a young nurse off to cry in the bathroom.
It’s especially difficult when you are a man that just doesn’t like playing those kinds of bullshit power struggle games, and also has the nasty habit of calling things like you see them. It’s been a difficult skill to learn, biting my tongue. I still struggle with it frequently. I’m old enough that I don’t play those games, and I tell people to fuck off. That’s when your attacker then plays the victim card and uses their victim status as a weapon.
My first experience with this was in nursing school, when a fellow student began bitching at me and calling me stupid, and I told her to shut the fuck up. I almost got kicked out of school after she went to the instructors and told them I was racist and sexist. For the rest of school, that woman (who also happened to be black) organized a “Hate on Divemedic” club amongst the other students and staff members of her own demographic.
If you get the feeling that I don’t like most women in the workplace, you would be correct. They spend more time setting up tribes, posturing, backstabbing, and putting on makeup than they do actually caring for patients. There is a lot less of that kind of bullshit in the ED, simply because we are too busy to have time for that shit. Let there be some down time, and the ED starts with it too.
It’s exhausting.
I got a message from a reader who is a nurse, talking about my last work post. The gist of it was “be careful making enemies of HR and training folks, they will screw you over.” You know what, that is 100% correct, nurses like that will find a way to get back at you. The difference now is that I am close enough to retirement that I just don’t care.
This past week, posting has been light. That’s because I have been orienting at the new job. I’ve been attending classes this past two weeks. There was the normal HR bs that you have to endure, some of it required by regulations, some of it the “rah-rah, this is the best company ever” garbage, IT policies, network security, social media policies, etc. That was two full work days.
Then there was compliance training for the new nurses at four different hospitals training on things like stroke protocols, HIPAA compliance, that sort of thing. It was all of the disciplines- medical/surgical, ICU, PACU, PCU, outpatient surgery, and more. Another three workdays. It was during this training that the nurses bound for the ED and the ICU argued with the nurses headed for other units, and with the nurse who was teaching the class. It was during the segment on testing blood sugar. The instructor said the unit can’t test blood sugar on a patient in cardiac arrest, but even if you could, it wouldn’t matter because you can’t give IV medications to someone without a pulse because no blood is moving. I was the first one to speak up. I pointed out that this is false, because we give all sorts of IV medication during a code- to include Calcium, Epinephrine, and even dextrose. The instructor told me I was wrong. The rest of the ED and ICU nurses chimed in their support, and the argument escalated from there. I pointed out that I am an ACLS instructor, board certified nurse- and I told her she was wrong. The instructor countered with “I am an instructor, too.” I bit off my first instinct to say “Not a very good one, then,” so instead I replied by reading directly from the American Heart Association’s page, proving her wrong. She still wouldn’t bend. That was when I noticed the woman who was standing in the corner, having walked in during our disagreement: My new boss, who was there to take me to lunch.
My new boss was cool with it and told me not to worry about the instructor and pointed out that there is a reason why she has never been in a critical care unit. The rest of the day went by quietly. The next day was spent in online training on ER specific policies.
We moved on to the second week- this one was in our actual workplace under instruction precepting and learning hospital protocols and procedures. What this meant in my case was my preceptor sat at the nurse’s station while I took care of our patients. Halfway through the day, I overheard the director telling my preceptor: “It’s his first day, you can’t just sit here without giving him any help our guidance.” To which the preceptor replied “He’s doing great.”
I worked four days in week two. My only weekday off (Thursday) was spent finishing up my network upgrades. I installed a supervised gateway and switch. Things went badly, and I wound up crashing the entire network. I spent over 8 hours getting everything back. A frustrating way to spend a day off. I was going to post about the left’s reaction to the submarine SINKEX, but Miguel beat me to it, so that post got tossed.
Monday starts my third and final week of training. There is a lot of information: Protocols, procedures, medication standing orders, those sorts of things. In the ER, there is too much going on, with much of it being time sensitive, so ED nurses enter their own orders for things. It’s one of the things I like about being an ED nurse- we have a lot of autonomy. It’s also why I carry a million bucks in malpractice insurance.
Since this is a PRN job, I already told them that, once my training is done, I am taking three weeks off. Three weeks of full time hours equals three weeks off. I am not about to work full time hours in what is supposed to be a part time position.
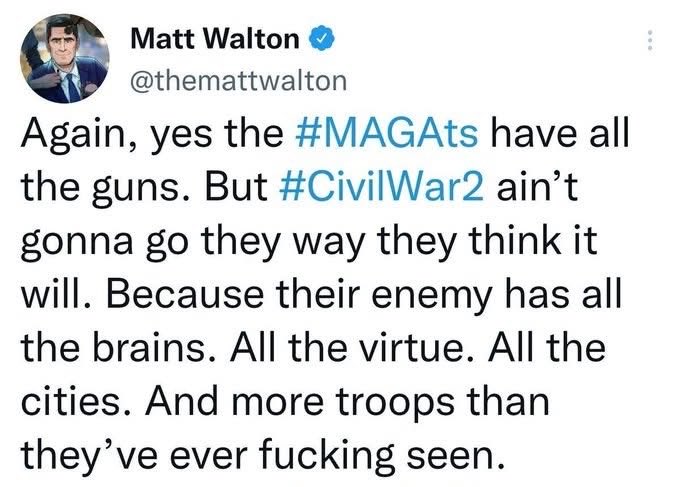
There is a segment of the left that wants a civil war. There is also one on the right that wants one. Both of those groups are delusional, because they both think the war will be short, and they will win.
Both sides are wrong. If there were a CW2 with similar casualty rates as the first one, we would see something on the order of 7 to 8 million dead and another million wounded. The majority of those deaths would be from disease and famine, not guns.
Still, this guy is a tool. They seem to think they will all be sitting in coffee shops, watching the military carry out their orders to wipe out their own families on CNN.
The reality will be much different. Cities would become disease infested wastelands once electric and water are cut off, and food deliveries stop. Some military units will simply desert their posts, taking weapons and gear with them. It would quickly degenerate into sectarian warfare.